



Advanced Microsurgical Resection, Awake Craniotomy & Precision Image-Guided Neuro-Navigation
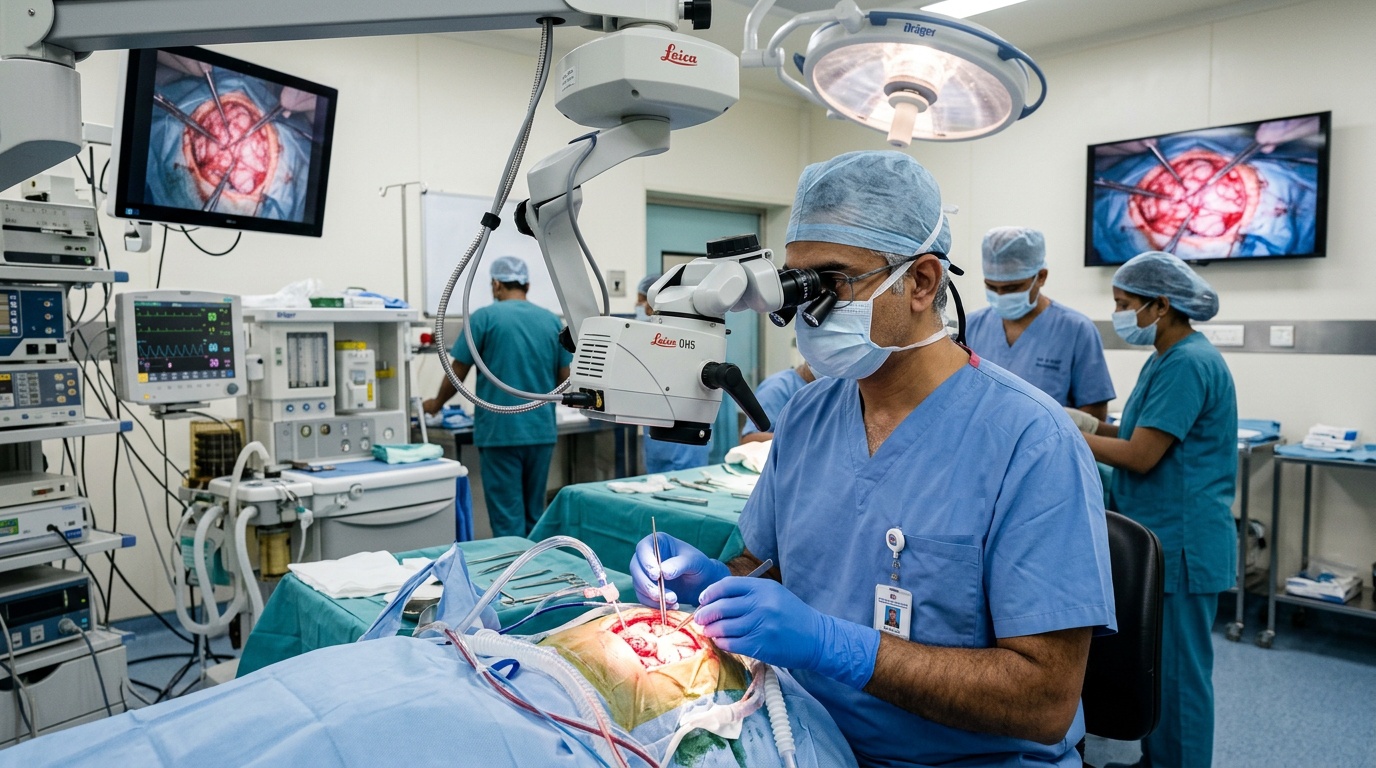
Brain Tumor Surgery & Neuro-Oncology
Clinical Overview & Pathophysiology
Brain tumors comprise a heterogeneous group of intracranial neoplasms originating either from the brain parenchyma and its surrounding structures (primary tumors) or via hematogenous dissemination from systemic malignancies (metastatic or secondary brain tumors). Dr. Ashok Kumar specializes in advanced neuro-oncological management, employing high-definition operative microscopes, intraoperative neuro-navigation, and neuromonitoring to achieve maximal safe resection while preserving critical neurological, motor, and linguistic functions. Common intracranial pathologies treated include High-Grade Gliomas (Glioblastoma Multiforme, Anaplastic Astrocytoma), Low-Grade Infiltrative Gliomas, Meningiomas (Convexity, Parasagittal, Skull Base, and Sphenoid Wing), Pituitary Neuroendocrine Tumors (PitNETs), Acoustic Neuromas (Vestibular Schwannomas), and secondary cerebral metastases.
Clinical Classifications & Pathological Subtypes
- Gliomas (Glioblastoma, Astrocytoma, Oligodendroglioma): Infiltrative parenchymal tumors requiring precision microsurgery and intraoperative functional mapping.
- Meningiomas (Convexity, Skull Base, Petroclival): Predominantly extra-axial, slow-growing neoplasms originating from arachnoid cap cells.
- Pituitary Adenomas / Sellar Masses: Endocrine-active or non-functioning lesions managed via minimally invasive endonasal transsphenoidal approaches.
- Acoustic Neuromas (Vestibular Schwannomas): Benign tumors of the 8th cranial nerve in the cerebellopontine angle requiring facial nerve preservation surgery.
- Secondary Metastatic Brain Lesions: Metastatic deposits managed by radical microsurgical excision or stereotactic radiosurgical planning.
Key Symptoms & Clinical Presentation
!Emergency Red Flags & Immediate Surgical Indications
Sudden explosive headache ("thunderclap" character), rapid alteration of sensorium, unequal or unreactive pupils (anisocoria), Cushing's triad (bradycardia, irregular respirations, severe hypertension indicating impending brain herniation). Immediate emergency neurosurgical decompression is mandatory.
Diagnostic & Neuro-Evaluation Workflow
Multi-Parametric 3T Brain MRI
High-resolution T1 with Gadolinium contrast, T2, FLAIR, and Susceptibility-Weighted Imaging (SWI) for tumor boundary demarcation.
MR Spectroscopy (MRS)
Biochemical metabolic profiling analyzing elevated Choline/Creatine ratios, depleted N-Acetylaspartate (NAA), and presence of lipid-lactate peaks.
Functional MRI (fMRI) & DTI Tractography
Non-invasive mapping of eloquent cortex (Broca's speech, Wernicke's area, primary motor cortex) and corticospinal motor tracts.
High-Resolution Contrast CT Brain
Assessment of hyperostosis, bony erosion at the skull base, tumor calcifications, and acute peritumoral hemorrhage.
Advanced Treatments & Procedures by Dr. Ashok Kumar
Image-Guided Microsurgical Craniotomy
Frameless stereotactic neuro-navigation with continuous real-time intraoperative tracking for millimeter-precise tumor resection.
Awake Craniotomy with Cortical Mapping
Specialized awake anesthesia protocol enabling continuous intraoperative language and motor testing during tumor excision in eloquent brain areas.
Endoscopic Endonasal Pituitary Surgery
Minimally invasive trans-sphenoidal corridor through the nasal cavity to resect pituitary adenomas with zero external facial incisions.
Intraoperative Neurophysiological Monitoring (IONM)
Continuous real-time Motor Evoked Potentials (MEP), Somatosensory Evoked Potentials (SSEP), and cranial nerve electromyography to prevent post-op neurological deficits.
Post-Operative Recovery & Long-Term Prognosis
Patients are monitored in the dedicated Neuro-Intensive Care Unit (Neuro-ICU) for 24 to 48 hours with continuous arterial blood pressure and ICP surveillance. Most patients are mobilized by post-op Day 2 and discharged within 4 to 6 days. Histopathological and molecular biomarker profiling (IDH1/2 mutation, MGMT methylation, 1p/19q codeletion) guides subsequent adjuvant therapies through our multidisciplinary tumor board.
Frequently Asked Questions (Clinical FAQs)
Authoritative, medically verified answers to critical clinical questions regarding symptoms, surgical safety, recovery timelines, and long-term prognosis.
How does Dr. Ashok Kumar protect speech and motor functions during brain tumor surgery?
What is the recovery timeline following a craniotomy for brain tumor removal?
What is the difference between a benign and malignant brain tumor regarding surgical approach?
Can a brain tumor be treated without open brain surgery?
What long-term surveillance protocol is required after brain tumor excision?
Brain Surgery & Cranial Conditions
- Brain Tumor Surgery & Neuro-Oncology
- Hydrocephalus Management: VP Shunt & ETV Surgery
- Head Injury & Emergency Neuro-Trauma Care
- Meningitis & Central Nervous System Infections
- Headache & Cranial Neuralgias: Neurosurgical Care
- Dizziness, Vertigo & Posterior Fossa Neuro-Evaluation
- Epilepsy & Seizure Disorders: Neurosurgical Evaluation
Why Choose Dr. Ashok Kumar
Emergency 24 Hours Dr. Ashok Kumar
Neuro-Spine OPD Location
Direct Consultation & Emergency
Email: dr.ashokkumar4108@gmail.com
Consultation Hours
Emergency Neuro-Trauma: 24/7 Open
